St. Christopher’s Hospital for Children named Claire Alminde permanent president on Thursday, following a period of leadership turmoil at the North Philadelphia safety-net institution.
Alminde, who will continue to serve as chief nursing officer, had taken over in January from another acting president.
“Claire brings a unique combination of frontline clinical experience and hospital leadership, along with firsthand knowledge of what it takes to operate a hospital like St. Chris that plays such a vital role in Philadelphia and beyond,” St. Chris said in an email.
One of Alminde’s tasks will be to work with leaders at Nemours Children’s Health, Jefferson Health, and Temple Health to build an alliance announced in July to secure the future of St. Chris, which struggles financially because most of its patients have low-paying Medicaid insurance.
St. Chris’ chief nursing officer, Claire Alminde, has been named president of the North Philadelphia safety-net provider.St. Christopher's Hospital for Children
Alminde was the third interim or acting executive appointed to the top management position at the nonprofit hospital since February 2024 and its fourth leader since 2020.
Drexel University and Tower Health have owned St. Chris in a 50-50 joint venture since 2019. Tower oversees day-to-day operations.
“After several years of leadership changes, this appointment gives St. Christopher’s strong, permanent leadership from someone who knows our hospital, our people and the community we serve incredibly well,” Tower CEO Michael Stern said in a message to employees. “Claire understands what makes St. Chris such a special place and what it will take to move us forward.”
The safety-net provider received a $76 million revenue boost from its inclusion for the first time in a program that taxes Philadelphia hospitals and uses the money to increase the government’s Medicaid funding for facilities that disproportionately care for low-income patients.
Independence Blue Cross, Philadelphia’s largest Medicare Advantage insurer, agreed to pay $22.5 million to settle a whistleblower lawsuit alleging that the company submitted inaccurate diagnoses for enrollees to increase payments, the U.S. Attorney for the Eastern District of Pennsylvania said Wednesday.
The IBX settlement, like several others this year, centers on how private Medicare insurers evaluate the health of the individuals in their plans, a process known as risk adjustment. The government gives insurers more money for sicker patients.
“This matter was not about the quality of care our members received. It involved differing views regarding certain documentation and reporting requirements under the Medicare Advantage risk adjustment program,” Independence said in an email. The company did not admit wrongdoing.
Federal officials said that for five years ending in 2020, IBX used nurses to review patient records and look for additional medical conditions that could be submitted to regulators. That generated additional payments for the insurer under Medicare Advantage’s risk adjustment models.
According to the government, the chart reviewers also found diagnoses that were not supported by the patients’ records, but IBX failed to withdraw those diagnoses. Had the company done so, it would have had to return money to the Centers for Medicare and Medicaid Services.
“Many major health plans have faced similar government scrutiny regarding Medicare Advantage risk adjustment requirements and practices, reflecting industry-wide challenges in the application of these standards,” Independence said in an email.
IBX’s settlement followed an agreement in May by Aetna, the Philadelphia region’s second-largest Medicare Advantage insurer, to pay $117.7 million for coding violations.
Nationally, two settlements this year topped half a billion dollars. Kaiser Permanente, a California-based insurance company with a large hospital business, agreed to a $556 million settlement in January, and Villages Health System LLC, a Florida provider group, settled for $541.5 million.
The whistleblower, a former IBX employee, will collect $3.8 million of the settlement amount. Government and company officials signed the settlement Sept. 11.
Temple University Health System saw a $22.7 million operating profit in the year that ended June 30, up slightly from $21.9 million in fiscal 2025, the North Philadelphia nonprofit told bondholders this week.
The result showed solid business operations while the system was “navigating intense professional liability and inflationary headwinds in a competitive Philadelphia healthcare market,” Temple said in an email to The Inquirer commenting on the results.
Here are more details:
Revenue: Temple’s total revenue rose nearly 10%, to $3.62 billion in fiscal 2026 from $3.29 billion the year before. Outpatient surgeries and cancer services were among the significant contributors to revenue growth from patient care, Temple said in its notice to bondholders.
Expenses: Insurance expenses climbed $19.3 million because of “higher professional liability costs related to inflationary legal expenses and the accelerated settlement of claims to mitigate rising awards by local courts,” Temple said.
Notable: Temple reported a 12% decline in cardiology procedures in fiscal 2026, to 4,654 from 5,274 the year before, because an unspecified number of physicians left. “As of late summer, 100% of these cardiology positions have been successfully filled,” Temple said.
Denise Fitzsimmons knew that removing the fast-growing lump above her eyebrow in 2024 didn’t eliminate the possibility that her melanoma could return.
But a clinical trial at Penn Medicine offered the 63-year-old grandmother from Birdsboro, Pa.,hope of a more enduring remission. It tested a novel vaccine, based on Penn’s groundbreaking mRNA research, that trains the patient’s immune system to find and kill cancer cells.
That technology has become the first mRNA cancer vaccine to succeed in a late-stage clinical trial, according to preliminary findings released last month by Merck and Moderna, the pharmaceutical giants developing it.
The vaccine extended the time a patient survived without their cancer returning or spreading, according to the companies, which announced Monday that they will share the full trialresults next month at the 2026 European Society for Medical Oncology meeting in Spain.
The drugmakers merely said that the results were positive. Without knowing the exact numbers involved, or how long the benefit lasted, it’s stillunknown if the results will prove clinically meaningful for patients. The companies also have not announced a commercial price tag for the therapy, called intismeran autogene, though similar immunotherapies can cost hundreds of thousands of dollars.
The trial could mark a turning point for mRNA technology, which has proven useful against infectious diseases but hadn’t had the same success in cancer.
Melanomas typically contain thousands of genetic mutations due to sun damage, making them an ideal target for the approach, which teaches the immune system to respond tounique markers on cancer cells.
“It’s a very big step forward after many negative studies in the last few years,” said Ravi Amaravadi, the lead investigator of the Penn trial site, one of more than 100 around the globe.
mRNA vaccines gained widespread attention in 2020 when used to develop the first immunizations for COVID-19. These shots used the mRNA platform developed by Nobel Prize winners Katalin Karikó and Drew Weissman, a University of Pennsylvania professor. Since then, mRNA vaccines for RSV and the flu have gained approval.
“This was kind of the wake-up call that RNA vaccines in cancer have an enormous future,” said Weissman, who was not involved in the trial and has no financialstake in Merck or Moderna.
Katalin Karikó and Drew Weissman were named winners of the 2023 Nobel Prize in Physiology or Medicine. The messenger RNA pioneers worked years to unlock an understanding of how to modify mRNA to make it an effective therapeutic – enabling a platform used to rapidly develop lifesaving vaccines amid the global COVID-19 pandemic.Tom Gralish / Staff Photographer
How the vaccine works
Melanoma is a serious type of skin cancer that develops when melanocytes — the cells that give skin its color — grow out of control.
This trial tested the vaccine in patients whose melanomas had already been removed through surgery. The goal was to destroy any remaining cancer cells and prevent the disease from returning or spreading to other parts of the body.
“It’s the deadliest form of skin cancer because it can metastasize,” Amaravadi said.
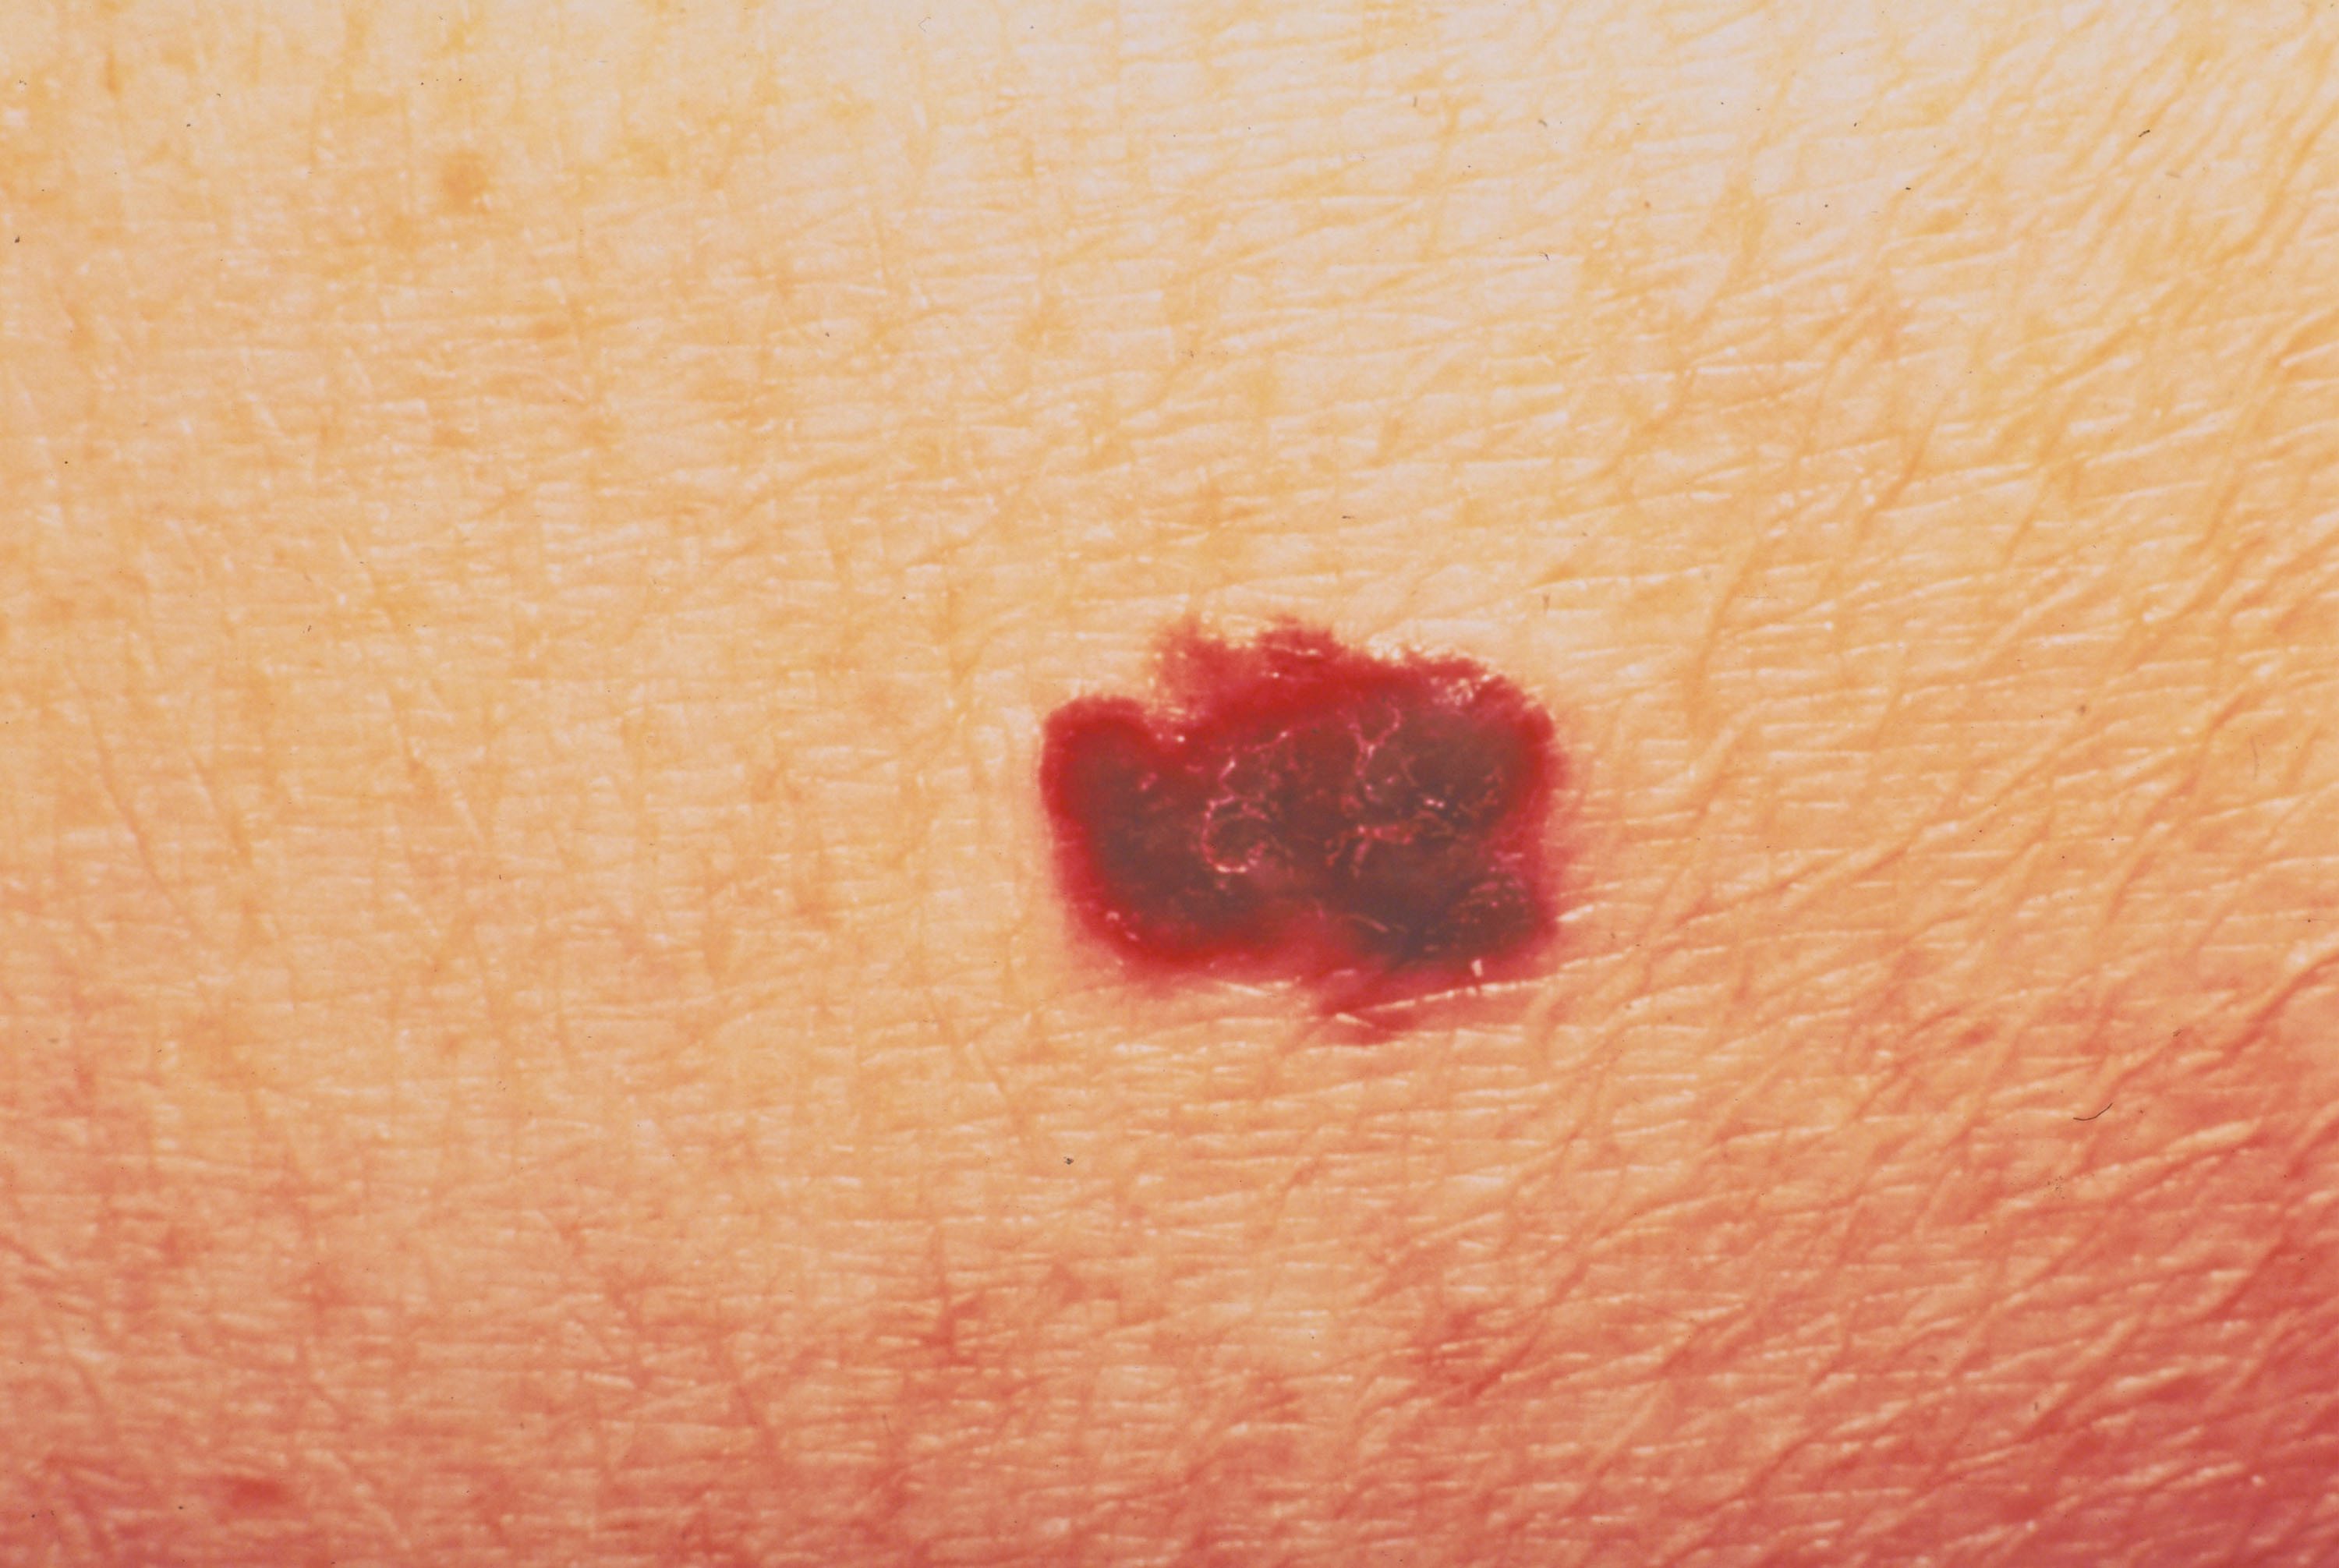
Detail of a person with a malignant melanoma, which is a malignant skin tumor that involves the skin cells that produce pigment. (American Cancer Society/Getty Images/TNS)Getty Images / MCT
Scientists personalized the vaccine for each patient by analyzing their tumor samples for unique genetic mutations. That enabled them to design mRNA — a molecule that carries genetic instructions — that would encode bits of protein that look like the tumor.
When the immune system encounters those proteins, it learns to recognize the cancer and attack it.
It’s similar to vaccines for the flu or COVID-19, which train the body to identify and fight off specific viruses.
If the immune system is trained in this way, it could produce a long-lasting memory against the cancer, Amaravadi said.
“We are now able to train the immune system to look for the tumor, arguably for the first time, in the most effective way,” Amaravadi said, referring to the mRNA platform.
That mRNA was loaded into a nanoparticle (which acted like a delivery truck hauling cargo) and injected into the arm as a shot.
Two-thirds of the 1,137 participants were randomly chosen to receive the vaccine in combination with Keytruda, a standard-of-care immunotherapy, while the remaining third received Keytruda alone.
The trial
Ravi Amaravadi led the trial site at Penn.Courtesy of Penn Medicine
Trial participants who received the vaccine had fewer metastases compared to patients who got the immunotherapy alone, Amaravadi said.
However, the company has only announced that the results were positive. Without knowing the data, it is hard to say whether the results are also clinically meaningful, Amaravadi said.
“We are hopeful we’re going to see the same absolute benefit when we see the data published,” he said.
Amaravadi also wants to see whether there were any unexpected side effects that patients should consider before taking the therapy.
Another data point of interest:How many patients agreed to receive the treatment but ultimately couldn’t receive it. In some cases, patients’ tumor samples were too small, didn’t contain enough usable genetic material, or were of too poor quality to actually make the treatment.
If this were a consistent problem, the technology used to analyze tumors’ genetic makeup would need to improve.
“It’s still a little bit of a bottleneck for some patients to get access to the treatment,” he said.
Denise Fitzsimmons of Birdsboro, Pa., is one of the participants at Penn’s trial site.Courtesy of Denise Fitzsimmons
Fitzsimmons, a grandmother living in the small Berks County town of Birdsboro, participated through Penn’s site. She doesn’t know whether she received the treatment or a placebo (that information is kept secret from both patients and researchers to avoid bias.)
But she recalls feeling flulike symptoms the day after each shot — including body aches and sweats — making her speculate that she may have received the vaccine. COVID-19 mRNA shots oftenprompt similar reactions.
Fitzsimmons has been cancer-free for the last two years.
“My fifth granddaughter is on her way,” she said. “So I have a lot to live for.”
The future of mRNA
RNA offers a few key advantages as a treatment.
Its effects are transient and controllable. The material lasts only a couple of days in the body before it degrades and disappears.
It’s also relatively easy to make.
“We made billions of doses of the COVID vaccine within a year. No other vaccine or therapeutic can be expanded that quickly,” Weissman said.
He believes RNA vaccines could benefit people with genetic mutations that put them at higher risk of cancer, such as BRCA carriers.
If people receive the vaccine before their tumors form, it could kill off any early cancer cells that arise.
“That way you prevent the cancer from ever forming, instead of trying to treat it after it’s already there,” Weissman said.
Conversely, he doesn’t think RNA vaccines would work well in someone whose advanced cancer cannot be removed. The immune system has a hard time killing large tumors, he explained.
This trial tested the vaccine as a follow-up to surgery, targeting leftover tumor cells.
Other ongoing trials aretesting mRNA vaccines in pancreatic, breast, colon, lung, prostate, and other cancer types.
Outside of cancer, clinical trials are testing mRNA vaccines for herpes viruses, malaria, tuberculosis, Zika, chikungunya, and norovirus. Scientists are also exploring whether mRNA technology could be used to treat allergic and autoimmune diseases.
The University of Pennsylvania picked the first three faculty-founded companies for early stage investments from its newly established $10 million StartUP fund, the university said Wednesday.
The three companies are working in maternal health, advanced radio-frequency filtering technology, and AI-powered drug discovery.
Each is receiving the maximum investment of $250,000 from the fund launched in December to make seed investments in companies founded by university researchers.
“Penn researchers are developing technologies with the potential to address some of the most important challenges facing society today, and many of these solutions have the potential to create entirely new markets,” John Swartley, Penn’s chief innovation officer, said in an announcement.
Here are some details on the three companies:
Vasowatch is developing a non-invasive monitoring system to predict the risk of maternal postpartum hemorrhage, a leading cause of maternal death. Its cofounders are Penn Nursing adjunct professor Stefanie Modri and former Penn Engineering faculty James Weimer. The company will use the money to fine-tune the product and to pay for a clinicaltrialanticipated to start next year.
OneFiltr, cofounded by Troy Olsson,aprofessor in the School of Engineering and Applied Science, has a compact device designed to allow a cell phone to isolate and process specific frequencies. The company will use its investment to further development of its device for evaluation by aerospace and defense companies.
Peptaris Inc. has an AI platform for evaluating and developing drugs based on peptides, which are building blocks for proteins. Cofounders are César de la Fuente and Marcelo Der Torossian Torres. The StartUP investment is part of a larger seed round that Peptaris is using refine its model and evaluate its first candidates. Peptaris said in an SEC filing June that it raised $4 million from investors.
Redeemer Health CEO Greg Wozniak has resigned from the financially troubled nonprofit Montgomery County health system after a little more than two years, Redeemer announced Thursday.
Replacing Wozniak on an interim basis is chief transformation officer Jim Logue, who has held the role since early 2025.
Redeemer has posted operating losses every fiscal year from 2017 to 2025. It hasn’t yet posted financial results for the fiscal year that ended in June.
“Jim and his team will work with our financial advisors and counsel to implement a reorganization of the Redeemer system to assure its continued viability and a sustainable business model,” board chair William R. Sasso said in an internal communication obtained by The Inquirer.
“This reorganization is expected to involve some significant organizational changes which will be announced in the coming weeks as they are finalized,” the note said.
More than four years ago, Redeemer announced that it was seeking what it called a “strategic partner” for its 239-bed hospital in Meadowbrook, near Abington, but nothing came of that effort.
Redeemer also operates a home care business, nursing homes, senior apartments.
Redeemer announced additional personnel changes Thursday in its internal communication, including the departure at the end of this month of chief financial officer Kim Cummings. Former CFO Michael Keen is returning to that position.
Another returning executive is Donald Friel, a former executive vice president tapped to assist Logue.
Diane Derr, who has been at Redeemer for 44 years, is being promoted to chief administrative officer from chief nursing officer.
Editors note: This article has been updated to correct Derr’s history with Redeemer.
Geisinger Health expects to lose more than $180 million in revenue next year when deep cuts to Medicaid start impacting the nonprofit health system with 10 hospitals in a largely rural stretch of central and northeastern Pennsylvania.
The Rural Health Transformation Program — meant to soften the blows from the cuts imposed by Congress under Republican’sso-called “One Big, Beautiful Bill Act” or H.R. 1 — offers limited relief.Geisinger expects to collect $6.7 million of the $193 million allotted to Pennsylvania.
“It’s given us some money for some critical infrastructure that we need,” such as a CT scanner or an MRI machine for hospitals that serve rural counties, CEO Terry Gilliland said in an interview last month.
But much of the money being distributed through the Rural Health Transformation Program, or RHTP, isn’t going to help rural hospitals because it wasn’t designed to do that. No more than 15% of the funding can be used to reimburse providers for healthcare services.
That has left Geisinger, which is owned by California-based Kaiser Health, in a tough spot: “H.R. 1 is taking a big old chunk out of our hide, and there’s just no way for RHTP to fill the hole,” he said.
Nationally, $911 billion in Medicaid cuts are anticipated over a decade, with $137 billion is expected to come from rural areas, according to KFF, a nonprofit that researches health policy. KFF’s analysis did not provide state estimates for rural losses.
The Rural Health Transformation Fund totals $50 billion over five years. Pennsylvania would receive $965 million if it were to get the same amount each year as it did this year. Philadelphia-area health systems haven’t received money from the fund yet, but could participate in the future through projects that benefit rural Pennsylvania.
Where the money is going
The rural health fund is an incomplete response to the revenue hole created by H.R. 1, said Katherine Hempstead, a senior policy officer at the Robert Wood Johnson Foundation, a Princeton-based philanthropy focused on healthcare advocacy and research.
“It is mostly targeted to upstream projects designed to make rural healthcare more efficient in the long run. They may or may not be successful,” she said.
All but $2 million went to technology and infrastructure projects, including critical needs like new roofs, HVAC systems, elevator repairs, and the repair of a collapsed sewer line.
On the technology side, new imaging equipment was popular in the first funding round.
With $3.7 million from that round, Geisinger got a new X-ray machine for its Bloomsburg hospital, new CT units for Jersey Shore and Lewisburg hospitals, and an upgraded compounding pharmacy for its flagship hospital in Danville.
Geisinger applied for $3 million from a forthcoming second round and plans to use the money for a special EMS vehicle, transport vans for senior care, telehealth equipment, and other capital equipment, if it is approved.
In addition to technology and infrastructure, Pennsylvania is focusing the rural funding on workforce development, maternal health services, behavioral health services, aging and access, and emergency medical services and transportation.
Geisinger’s approach to filling its financial hole
Geisinger’s estimated $180 million revenue loss next year has three main drivers. They are limits on how much federal money the state can generate through provider taxes, changes to the supplemental payments for hospitals with large numbers of Medicaid patients, and an increase in the uninsured population caused by new Medicaid enrollment rules.
In 2025, Geisinger had about $10 billion in revenue. That’s up from $7.7 billion in 2023, that last full year before it became part of Risant Health, a new nonprofit created by Kaiser in 2023 to acquire community health systems.
Already this year, Geisinger has seen a $10 million a month increase in charity care and bad debt write-offs, Gilliland said, which he attributed to people not being able to afford individual Affordable Care Act plans after the enhanced tax subsidies expired.
“How many more of these hits can I take? The answer is not very many,” Gilliland said.
The health system is focused on becoming more efficient.
“There’s some optimism that says we could find some way to have artificial intelligence do some of the tasks that we typically throw humans at,” Gilliland said.
He hopes to avoid want layoffs, given that Geisinger is often the largest employer in its communities.
“I’d really like to figure out ways to fill the hole without having people lose their jobs because that has a much more devastating impact on the local economy,” he said.
Highmark reached an agreement to keep Rothman Orthopaedics in network for Pennsylvania customers of Highmark Blue Shield plans and federal employee health programs after Oct. 1, the two companies said Wednesday.
The Pittsburgh-based insurer had issued a termination notice over the summer, alleging that about a half-dozen Rothman surgeons were abusing a federal process designed to protect patients from unforeseen out-of-network bills.
The dispute centered on the use of out-of-network physician assistants by Rothman surgeons who do not have residents or fellows working for them and need help treating patients.
Highmark said that the practice violated a contract that took effect at the beginning of last year and that the use of arbitration under the federal No Surprises Act generated extraordinarily large payments for the physician assistants.
The physician assistants worked for separate company that Rothman, a practice, had no control over, a Rothman official said earlier this month.
Pay and benefits typically account for more than half the total costs in hospital systems at a time when healthcare costs are rising sharply in the Philadelphia region and nationally.
Local nonprofit health systems reported compensation ranging from $1.2 million to $3.7 million in 2024 for the 100 highest-paid employees listed in their most recent federal nonprofit tax returns. The ranking excludes system CEOs.
Meanwhile, employers are expecting insurance increases approaching 10% for the coming year, according to several national surveys by benefits consultants. Experts cite increased use of healthcare services, widespread use of expensive specialty drugs, and rising hospital prices as key factors leading to overall rising benefit costs.
Clinicians accounted for 60 spots in The Inquirer’s top 100 ranking, which is based on compensation reported in dozens of 990 tax forms from Philadelphia-area hospitals, affiliated physician groups, and other related entities.
Highly specialized neurosurgeons accounted for the highest number of top-paid clinicians, followed by cardiac and cardiothoracic surgeons and orthopedic surgeons.
Chief financial officers and chief operating officers were well represented in the management ranks.
The region’s largest health system also claimed its highest-paid non-CEO, Jefferson Health president and physician Baligh R. Yehia. His $3.7 million in compensation also topped that of all but two CEOs, as disclosed in a previous Inquirer analysis.
Thomas Jefferson University, which is Jefferson Health’s parent entity, had 30 executives and physicians in The Inquirer’s top 100. The Jefferson group includes four executives who left during or before 2024, but not salaries reported through the Lehigh Valley Health Network, which Jefferson acquired in August of that year.
Children’s Hospital of Philadelphia had the second-largest number of employees in the top 100, with 18, including surgeons and numerous top executives, such as CFO, general counsel, and head of human resources.
Virtua was third, with nine employees, mainly surgeons.
Across the region, 176 nonprofit health system employees received at least $1 million in total compensation in 2024. That amounts to one in five employees in The Inquirer’s database of more than 800 people.
IRS rules require nonprofits to report compensation for officers, highest-paid employees, and employees with a certain level of responsibility.
(function(){function e(){window.addEventListener(`message`,function(e){if(e.data[`datawrapper-height`]!==void 0){var t=document.querySelectorAll(`iframe`);for(var n in e.data[`datawrapper-height`])for(var r=0,i;i=t[r];r++)if(i.contentWindow===e.source){var a=e.data[`datawrapper-height`][n]+`px`;i.style.height=a}}})}e()})();
The two busiest surgery centers in the Philadelphia region last year were operated by Penn Medicine in Radnor and Jefferson Health in Center City.
Such facilities have grown increasingly popular as a cost-saving option for procedures that do not require intensive hospital resources or overnight stays.
While they offer convenience, the facilities operated by Penn and Jefferson both count as hospital departments for billing purposes, which means they cost more than surgery centers operated by independent physicians or other companies.
Penn Medicine Radnor Surgery Center operates within a large outpatient facility near the intersection of I-476 and Route 30. It logged 12,464 surgical visits in 2025, up from 8,961 the year before, according to data published last month by the Pennsylvania Department of Health.
Penn attributed the growth to the addition of new gastroenterologists in Radnor to perform colonoscopies, upper endoscopies, and other procedures. Colonoscopies, in particular, account for a large portion of the overall volume in surgery centers outside hospitals.
Jefferson Surgery Center was close behind, with 12,261 surgical visits, up from 2,639 in 2024. It sits within the Honickman Center, which opened in 2024 at 1101 Chestnut St. in Philadelphia. Jefferson has gradually expanded the array of surgical services offered there.
“Growth has been driven by both increasing patient demand and the strategic transition of services from other Jefferson locations, allowing us to provide care in a state-of-the-art outpatient environment,” Jefferson said in an email.
Other fast-growing surgery centers include two independently operated facilities focused on orthopedics, Premier at Exton Surgery Center in Exton and Restore Orthopaedic Surgical Institute in Chadds Ford.
(function(){function e(){window.addEventListener(`message`,function(e){if(e.data[`datawrapper-height`]!==void 0){var t=document.querySelectorAll(`iframe`);for(var n in e.data[`datawrapper-height`])for(var r=0,i;i=t[r];r++)if(i.contentWindow===e.source){var a=e.data[`datawrapper-height`][n]+`px`;i.style.height=a}}})}e()})();
Surgery center ownership matters
Even though the Penn and Jefferson outpatient facilities are not in hospitals, their ownership by large hospital systems enables providers to get paid as if they were located inside the Hospital of the University of Pennsylvania or Thomas Jefferson University Hospital.
Hospital outpatient department billing rates are sometimes twice as much as the rates paid to independent surgery centers.
For example, surgery to remove torn cartilage from a knee can cost $7,190 when performed on an outpatient basis in a hospital, nearly three times the $2,477 cost in ambulatory surgery centers (ASCs), according to Philadelphia-area commercial insurance averages from Turquoise Health.
Health insurers Independence Blue Cross and Highmark have implemented policies this year seeking to save money for employers and patients by moving care out of hospitals and into ambulatory surgery centers or ASCs. Both insurers say they will only pay for certain procedures if they are done in an ASC.
But it’s not enough to move surgeries to a setting outside a hospital, given the hospital-like billing status of certain surgery centers.
“The cost savings from an ASC depend on the facility’s ownership, licensing, and billing model,” Richard Snyder, IBX’s chief operating officer, said in a email to The Inquirer.
IBX would like to see more ASCs in its Southeastern Pennsylvania market and is “prepared to help catalyze growth through continued value-based arrangements, strategic partnerships, and investments,” Snyder said.
Litigation over ASCs and other policies
In a July lawsuit against IBX, Jefferson claimed that the insurer’s ASC policy amounted to a change to the financial terms of their contract that needed to be negotiated.
The lawsuit said that ASC mandate will cost the health system $35.4 million, but doesn’t specify over what time period.
IBX filed a motion last weekto dismiss the lawsuit, which was moved to U.S. District Court in Philadelphia from the Philadelphia Court of Common Pleas.
The insurer says that the lawsuit was premature because Jefferson filed it before completing a contractual process designed to resolve such policy conflicts.